 | ||||||
| | ||||||
Hospitalogists, On Tuesday, I ran through every health system deal from the past month (by the way, my archive of past sends is back up on the site! Check it out and let me know what you think), plus the services deals happening around them. Today's part 2 where I attempt to distill down some of the trends and analysis. PS - Tomorrow! at 12 CT! I’m discussing the capital markets and changing M&A environment for PPMs, including implications for health systems, during an expert session tomorrow with VMG Health’s Colin McDermott and Cordell Mack. Don’t miss it - the event is open to all Hospitalogists! Register here. If that link doesn’t work, reply and I’ll manually add you  Was this email forwarded to you? Sponsored by SmarterDx Health systems don’t need another AI promise. They need the revenue they’ve already earned, especially with more cuts on the horizon. Health Systems are emerging as strategic buyers while payors continue to divest.In January 2025, Bain Capital made a non-binding offer of $25.75 a share to take Surgery Partners private (Surgery Partners). 5 months later, a special committee ended the process, concluding its standalone plan was worth more (Surgery Partners). Then on Oct. 26, Surgery Partners announced it had agreed to be acquired by HealthSpan Partners, an affiliate of Bon Secours Mercy Health, for $23.50 a share (8-K). Bain, notably, is rolling its ~39% stake into the deal and sticking around as a partner. So the private equity firm couldn't get it done, and a Catholic health system did, at $2.25 a share less. For most of the last decade, the strategic buyer of physician groups, clinics and surgery centers was a vertically integrated payor with a balance sheet and a growth target. That era is over, or at the very least, waning at present. Health systems and drug distributors are now the strategic buyers of care delivery assets, while the integrated behemoths prune their footprints, close clinics and hand the capital bill to partners like BlackRock. And the systems doing the buying have mostly stopped buying their crosstown rival. They're crossing state lines, buying ambulatory platforms, pulling functions like revenue cycle back in-house, and trying to get bigger (well…denser) before HR-1's Medicaid cuts start phasing in. Under all of it sits a quieter shift in how systems keep score. I'll get there. The strategic buyers in late 2026Ascension closed on AmSurg June 4 for ~$3.8B, per its audited financials, picking up 250+ ASCs across 34 states (bringing Ascension's total to 300+). 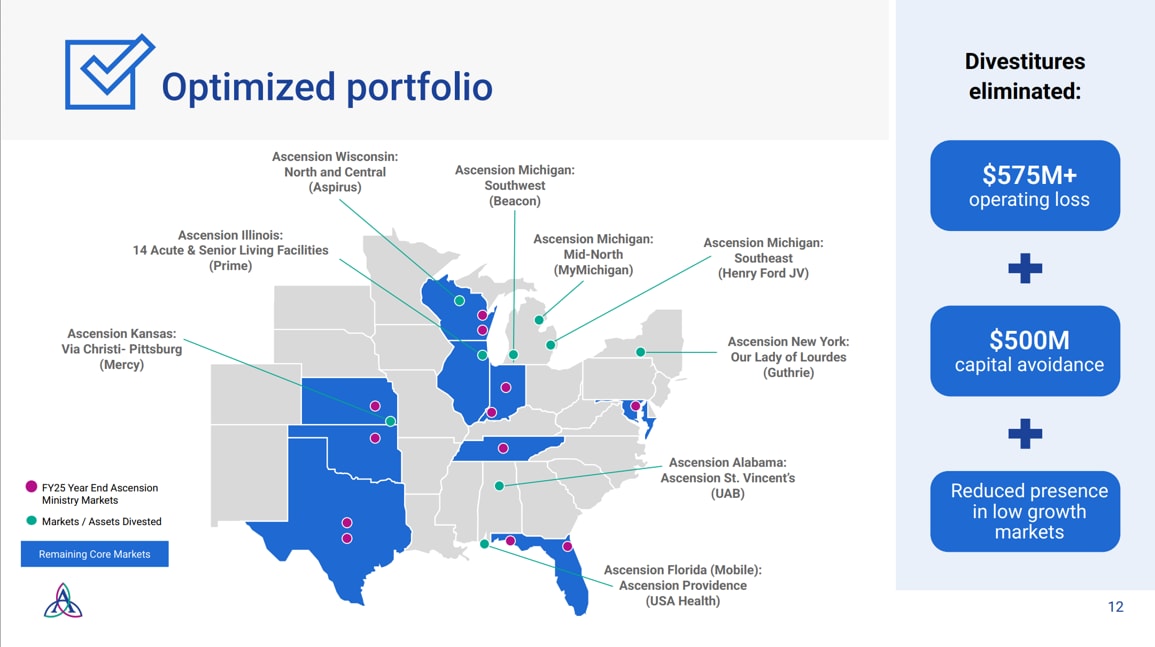 In the 3 years before that, Ascension went from ~139 hospitals to ~90 wholly owned or consolidated ones. 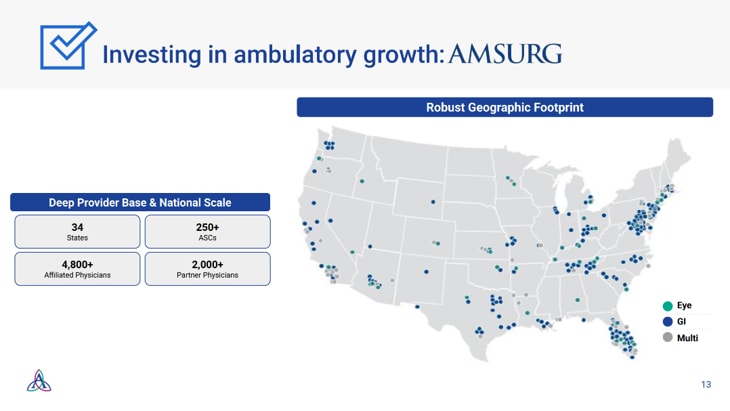 Sell hospitals, buy surgery centers. BSMH just made the same bet at a bigger number: ~$5.7B of enterprise value for 200+ locations in 30 states and ~5,000 affiliated physicians. Meanwhile HCA, which has never needed a partner to build anything, wants 20 outpatient facilities per hospital by the end of the decade, up from ~12 in 2023 and 14+ today, per CFO Mike Marks. HCA's ~150 ASCs, in its own words, "help us secure our surgeons" as a physician alignment strategy. M&A shaped around the concept of density in core markets. 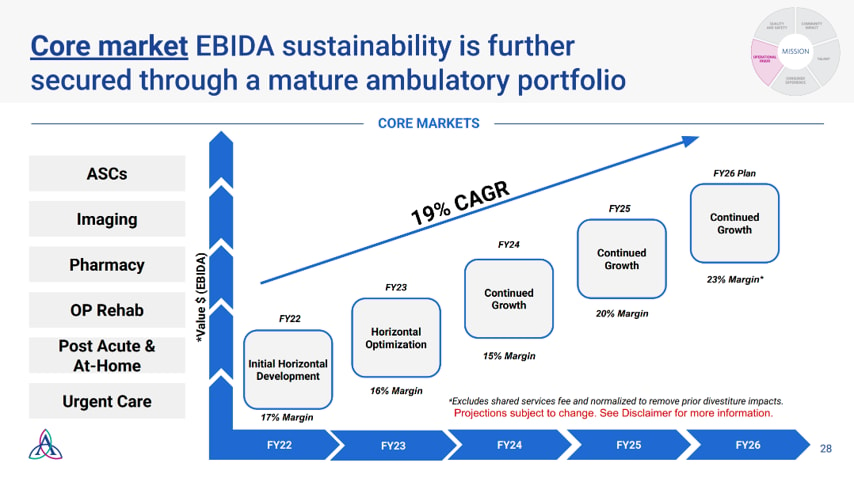 Drug distributors are the other strategic buyer, and they're still the most underrated buyers in healthcare with seemingly blank checkbooks. Oncology, retina, GI and urology practices are where expensive specialty drugs get bought, administered and billed. Own the practice and you own the channel, as well as areas of high specialty drug spend (ding ding ding): 
Now look at who's selling.
Vertical integration! So many synergies! Sure, Horizon BCBSNJ just agreed to buy Summit Health New Jersey. But a home-state Blue buying a big medical group in its own backyard is a network and access play. It's a different animal from a national payor stitching together care delivery across dozens of states, and it’s a market signal that M&A is moving more toward this regional, density strategy rather than national scale, grow at all costs type of thinking. So we’ve got some conference realignment. Payors built the care delivery empires of the last decade. Health systems and distributors are buying the pieces now, with the obvious counterforce being physician comp inflation year in and year out. Consolidating before the cliff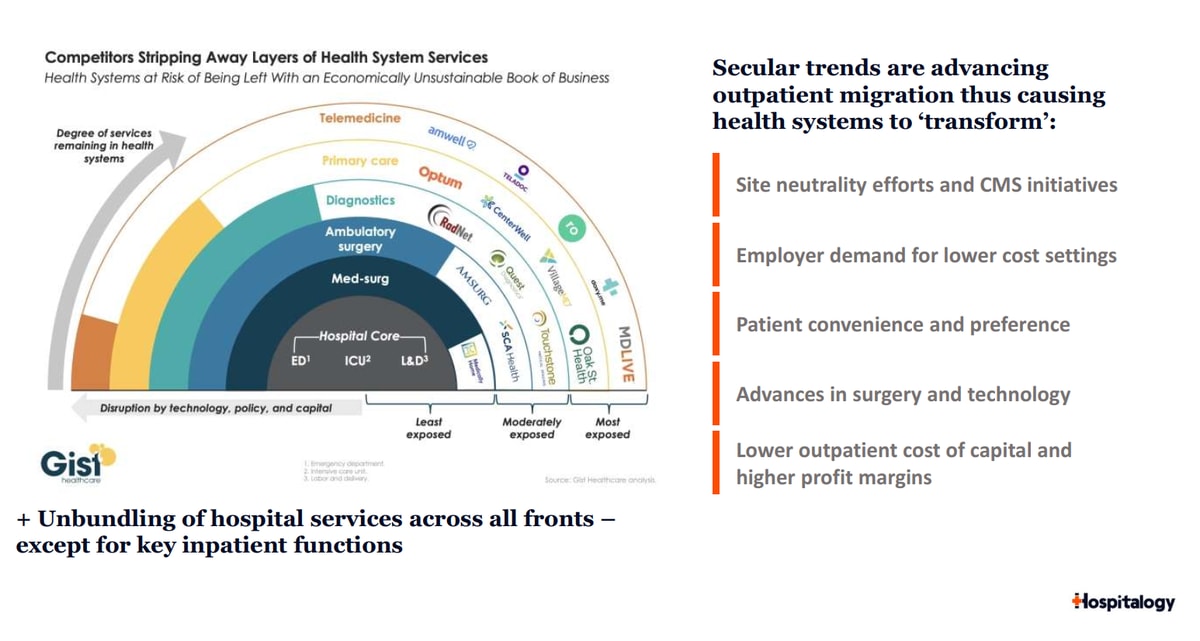 Fiscal 2028 is circled on every health system CFO's calendar as policy cuts and change phase-in. Here's what HR-1 puts on it:
KFF pegs the law's federal health spending cuts at more than $1T, with ~10M more uninsured. Enhanced ACA premium tax credits expired at the end of 2025 as all Hospitalogists should know by now. And the pain is already showing up system by system: Integris expects more than $130M in 2026 revenue losses tied to Medicare and Medicaid cuts, plus planned service line and staff reductions; Kaufman Hall noted nearly 43% of hospitals are operating at a loss. So most systems plan to grow their way out of it. And the fastest way to grow is to buy, or to be bought by someone who can fund the next 5 years. Consolidate now, and lock in the economics before the cuts phase in. Look at the calendar, too. Sutter–Allina is expected to close by year-end. HealthPartners–Essentia wants to be effective Jan. 1. Humana's CenterWell JV is slated for Q4. Endeavor–RUSH, Risant–Integris and Surgery Partners all point to early 2027. A slew of other deals announced and/or closing in the back half of 26 or early 27. Part of that is the state review clock. Ropes & Gray's tracker lists 11 states with transaction review laws, and Bass, Berry & Sims counts 8 that enacted new laws or rules in 2026 alone, California's AB 1415 and Massachusetts' 958 CMR 7.00 among them. Oregon's review can run up to 180 days. Massachusetts can push a closing out up to 215 days. In those states, if you want to close by Jan. 1, you'd better sign in the spring. I'll be honest, the midterm half of my timing thesis is more anecdotal and vibes-based. But nobody wants a signed deal sitting in a review queue while the politics shift underneath it. In Minnesota, Sutter–Allina and HealthPartners–Essentia are both under review by an attorney general who's on the ballot Nov. 3. Conference realignment, healthcare editionNow, the type of consolidation is the interesting part. No longer are we seeing much intra-market consolidation. We're seeing contiguous market consolidation, cross-market mega mergers, moves into vertically integrated assets like ASCs and RCM, and a healthy dose of corporate restructuring. Kaufman Hall and Vizient put it this way in their Q3 report: these alignments "center less on local market concentration." Oregon, USC and Washington play Big Ten football now (traveling to Rutgers, insanity). Texas is in the SEC. Nobody blinks anymore. Sutter, a California system, is adding Minnesota's Allina as its "Upper Midwest Division." Same energy. I actually can’t believe how interesting of a parallel that is. Here’s a quick breakdown of health system M&A archetypes as I see them:
Endeavor–RUSH is an interesting exception, perhaps considered contiguous. Same metro. And on announcement day, nurses' union leaders urged regulators to block any merger that doesn't guarantee services are protected (Chicago Sun-Times). Fee for service heads in beds is a lagging indicatorOutpatient migration has a federal rulebook now.
Market forces are pushing the same direction. Affordability has self-insured employers experimenting with direct contracting: 32BJ Health Fund and Northwell Direct billed their agreement as the largest direct healthcare contract of its kind (Business Wire). And patients increasingly act like consumers, comparing price and convenience before they ever pick a site of care.  So health systems are reshaping their portfolios around where care is going: physician alignment, ambulatory assets, and a hard rethink of what gets built and where. Consequently, as technology and market forces reshape care and the patient experience, leaders are deploying AI where it boosts throughput and collections: ambient documentation, referral management, scheduling, prior auth. More ambitious systems are using it to connect the longitudinal patient journey instead of optimizing a single service line or point of care. Many leading health systems are thinking of AI investment as a portfolio, spread between short-term, high hard ROI (coding) and longer term, ecosystem-enabling efforts (nursing handoffs, access). Stated differently, the KPIs are shifting from heads in beds to patient loyalty and LTV:CAC. I've framed this before as whole-house math: what matters is the lifetime value of a household's care, captured across every site you own, against what it costs to win and keep that household. In that world, the system that keeps its surgeons keeps the household, which is why HCA cares a LOT about securing them. But more importantly, you start straying from point-of-care site optimization into patient journey optimization, and reshaping assets and experience around that idea instead. This is a significant culture shift for the health systems that choose to disrupt themselves this way. Fee for service success is now a lagging indicator. But change is here, and change is necessary. 4 health system archetypes taking shape (maybe 5) I asked AI for some health system archetypes and I thought they were pretty good for late 2026. Let me know what you guys think:
I'm curious what you think. Which archetype is your system, which one does your board think it is, and what am I missing? Hit reply and tell me.  Regardless, regulators will rule on the combinations. And whether any of them work comes down to the actual blocking and tackling, culture, process, and integration efforts. Which makes me wonder how many of these will look like 1 system in 2030, and how many will still be a collection of logos sharing a CEO. This is my read, and these are my rambling thoughts on a very busy quarter. If I misread a deal or a number (which is possible; I'm fallible), hit me with it. Let’s get after it. TOP READS AND RESOURCES Qventus' Care Gap and Coding Automation Suite surfaces missed diagnoses at admission and orchestrates clinical response, documentation, and coding inside the EHR, so patients get treated sooner and hospitals capture the reimbursement they've earned. Read my article.* A framework worth stealing: This piece from McKinsey isn’t about healthcare, but it should be on every health system CEO’s reading list. McKinsey’s thesis is that incumbents have a hidden advantage in decades of proprietary data and institutional knowledge, and an “AI OS” is how you put it to work across the org instead of in scattered pilots. Imagine what that looks like for a system juggling payer contracts, labor costs, and service line strategy in separate silos. Prior auth has long been healthcare’s favorite punching bag, so it’s refreshing to see real-world data points in this Q&A between Healthcare Dive and Epic’s Ryan Bohochik. Bohochik says early adopters are seeing less administrative overhead, and one state Blue Cross Blue Shield plan using AI to summarize authorizations is saving about 15 minutes per case. His broader point: the APIs are not the endpoint, they’re the infrastructure that makes further automation possible. Table stakes, but a real step forward. CMS wants to stop paying providers for remote patient monitoring delivered through third-party vendors, and this KFF Health News piece lays out why that could land hard in rural America. *This resource is brought to you by one of my brand partners who help make this newsletter possible! Thanks for the read! Let me know what you thought by replying back to this email. — Blake | ||||||
|



